Section: Skin and soft tissue Sub-section: Skin infections and breakdown Curriculum: Curriculum, page 53
Definition
- A necrotizing and rapidly progressing infection of the perineum, genitalia ± abdo wall
- Originally described as scrotal gangrene:
- Acute onset, rapid advance, no apparent cause
Incidence
- Mean age at presentation 45-60
- Frequently associated with DM/DKA
- Or may complicate otherwise minor anorectal/perineal sepsis, trauma or surgery or urinary infection
- Esp. in immunocompromised patient
Aetiology/Predisposing Factors
- Immune suppression:
- AIDS, malignant haematological disease, chronic EtOH
- DM (40-75% of pts diabetic)
- HT & cardiac disease
- Obesity
- Localised trauma
- Local Infection
- Orchid/epididymitis, paraphimosis, perirectal/anal infection
- Local surgical procedures
- e.g. Circumcision, hernia repair
- Poor hygiene
- Smoking
- PVD
Clinical
- Rapidly spreading cellulitis of perineum
- Can spread up abdominal wall
- But not to back unless severe, as Colle’s Fascia fuses laterally
- Symptoms
- Severe perineal pain, fever, systemic toxicity
Pathology
- Polymicrobial infections
- Gas formation common - Clostridia perfringens
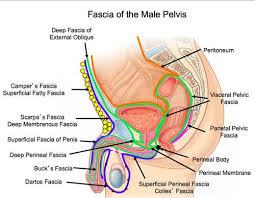
Anatomical Barriers to Spread
- Colle’s Fascia
- Superficial Perineal Fascia
- Projected into penile and scrotal extensions
- Buck’s Fascia of Penis and Scrotum
- Continuation of Colle’s and Scarpa’s fascia
- Scarpa’s Fascia of anterior abdominal wall
- As a result
- Testes and epididymis are commonly not affected
- Also blood supply separate
Investigations
- Clinical diagnosis
- FBC, UEC, CRP,
- Blood cultures
- Specific micro-organism rarely identified
Management
- Broad antibiotic combination
- Penicillin
- Metronidazole
- (3rd generation) Cephalosporin
- Aminoglycosides
- Clindamycin
- Wide excision of all necrotic tissue
- With late closure by a split-thickness skin graft
- Although the testicles may become exposed
- After sloughing of the overlying scrotal skin or following debridement
- Usually survive intact, with independent blood supply
- Cords are likewise usually spared
- ± Colostomy to prevent contamination of the wound in the post-op period
- Hyperbaric oxygen considered for Clostridium
- ↓ mortality
- Prognosis poor
- 75% mortality rate