Section: Skin and soft tissue Sub-section: Skin infections and breakdown Curriculum: Curriculum, page 53
Section: Skin and soft tissue Sub-section: Skin infections and breakdown Curriculum:
Classification Wounds
- Can either be by:
- Type of wound
- Mechanism of Injury
Type of Wound
- Type 1 (Clean)
- Type 2 (Clean contaminated)
- Type 3 (Contaminated)
- Type 4 (Dirty)
Type 1 (Clean)
- Made in sterile conditions, with no contaminated tissue being breached
- Elective surgical wounds
- Body wall and non-contaminated deep tissues
- Minimal airborne contamination
- Negligible risk of infection (< 2%)
- Primary wound closure is method of choice
Type 2 (Clean Contaminated)
- Minimally contaminated wounds
- Tidy incisional wounds inflicted by sharp cutting instrument in non-sterile fashion
- Or sterile surgical instruments in a non-infected tract
- Small bowel, biliary, bronchial tree etc.
- Minimal macroscopic contamination
- Risk of infection still low (1-5%)
- Should still be closed primarily after some form of wound toilet
Type 3 (Contaminated)
- Untidy and contaminated wounds created in a dirty environment
- Wounds in operative procedures where an infected tract or dirty tract is opened
- Infected bronchial tree or infected urological tract
- Dirty large bowel or rectum
- Wounds in procedures where gross contamination from a non-infected tract
- Abscess
- May require wide debridement and copious irrigation before delayed primary, or primary closure
- Significant risk of wound infection (2-25%)
Type 4 (Dirty)
- Infected, contaminated or devitalised wounds
- Open wounds of duration > 12 hours
- Operative wounds in areas of gross septic or faecal contamination
- Severe tissue damage and excessive ischaemic tissue
- Incl. severe crush injuries
- Should never be closed unless confidently converted to type 1 or 2 wound by wide debridement and irrigation
- Often requires healing by delayed primary closure or secondary intention
- Infection rates high (near 50%)
- Risk of severe synergistic infections (gangrene) or other necrotising infections exists
Surgical Site Infection Classification
- Superficial Incisional SSI
- Deep Incisional SSI
- Organ/Space SSI
Mechanism of Injury
Blunt Injury
- Deceleration with significant transfer of kinetic energy
- Object striking person
- Injury usually limited to site of impact
- Skin and soft tissue compressed
- Burst with stellate laceration
- Underlying blood vessels may burst with subsequent haemorrhage and contusions
- Energy transfer through tissue can compress/damage bone, underling blood vessels, or tissue (brain/viscera)
- Brain can be forced against back of skull (Contra-coup injury)
- Moving person striking object
- Get deceleration trauma, abnormal deformation of bones and joints
- Also get deceleration injuries of viscera
- Thoracic aorta at ligamentum arteriosum
- Small bowel bucket handle injury
- Avulsion injuries etc.
Penetrating Injury
- Can be simple or complex
- Main difference is the kinetic energy of the injury
- Low energy wounds
- Anything up to a small calibre (.22) bullet
- Cause injury in the line of penetration
- High velocity injuries
- Transfer much more energy
- Cause wide cavitation due to pressure wave created by passage through tissue
- Damage to, and devascularisation of, nearby tissues
Thermal Injury
- Can be
- Hot
- Cold
- Dry heat causes burn
- Moist heat causes scold
- Prolonged cold exposure causes chilblains
- Freezing of tissue by cold causes frostbite
Heat injury
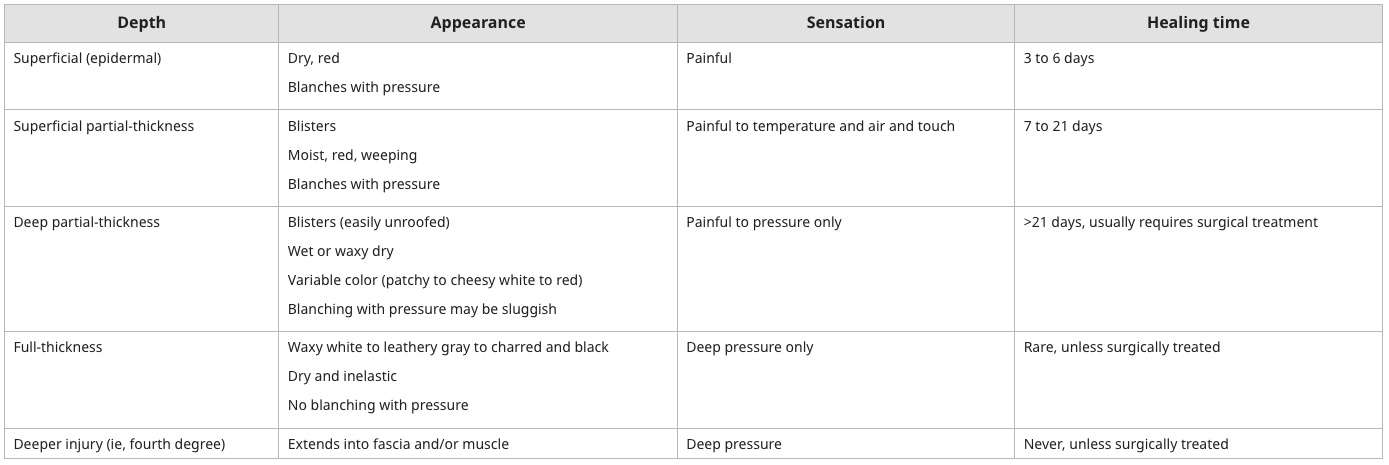
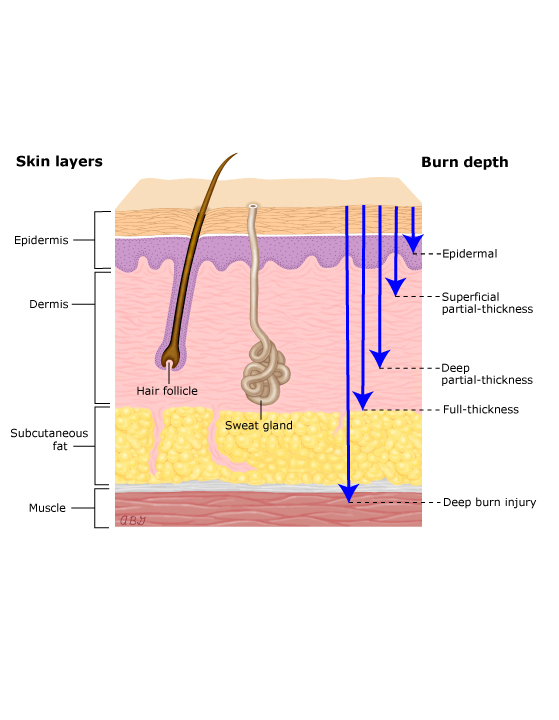
- Pathology of burns and scalds are Coagulative necrosis of epidermis and dermis to a variable depth
- Classification
- Superficial - only epidermis
- Partial - epidermis and portions of dermis
- Superficial partial - superficial dermis
- Deep partial - deep dermis
- Full-thickness - all dermis and down to subcutaneous tissue
Rule of 9’s
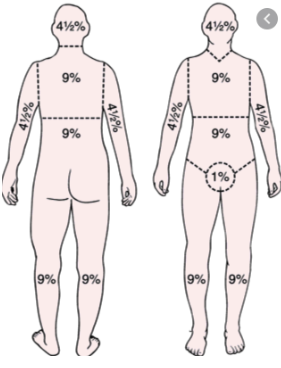
Cold Injury
- Final effect very similar to hot injury – tissue necrosis
- But not coagulative from the start
- Prolonged exposure to cold but not freezing
- Dry – Chilblains
- Wet - Trench Foot
- Frostbite – actual freezing of body tissues
- Extent of damage worse due to rapidity of freezing and duration frozen
- Injury caused by freezing AND by subsequent thawing
- Pathogenesis: Intracellular ice crystallisation, cellular dehydration (and lysis) and microvascular thrombosis
- Warming can cause further injury, but is essential part of treatment
- Don’t debride until all tissue is warmed and assessment of unviable tissue can be made
- Enables minimization of debridement
Frostbite Grading System
- First Degree
- Very superficial
- Hyperaemia, oedema, minimal necrosis
- Second Degree
- Partial thickness
- Hyperaemia, rapid oedema, large blisters
- Necrosis present
- Sensation intact
- Third Degree
- Full thickness skin injury
- Pale with slow onset of oedema
- Eventual necrosis
- Sensation lost
- Fourth Degree
- Full skin thickness and deep tissues
- Limb infarction
- Requires amputation
Mechanisms
- Direct cold damage to cells
- Direct cell damage from ice crystals, which includes protein and lipid disruption and electrolyte shifts
- Indirect cell damage from intracellular dehydration caused by the presence of extracellular ice crystals
- Microvascular stasis, thrombus formation, embolic events in the microvasculature, and ischemia
- Reperfusion inflammatory injury with ultimate tissue necrosis
Four phases
- Prefreeze phase - This phase consists of superficial tissue cooling, which results in the increased blood viscosity, microvascular constriction, ischemia, and endothelial plasma leakage that precede the formation of ice crystals
- Freeze-thaw phase - This phase consists of ice crystal formation, more in the extracellular space than in the intracellular space. Thawing may induce reperfusion injury with an inflammatory response.
- Vascular stasis phase - This phase consists of arteriovenous shunting at the margin between injured and noninjured tissue. Vasoconstriction may alternate with vasodilation. This may result in a combination of both progressive microvasculature erythrocyte sludging, stasis, coagulation, and thrombus formation, and leakage of blood from the vessels.
- Late progressive ischemia phase - This phase consists of thrombus-induced inflammation, hypoxia, and anaerobic metabolism leading to tissue necrosis
Management
- Simultaneous assessment and resuscitation
- ABCDE as per EMST
- Rapid rewarming – submerge is 40 degree water for up to 1 hour. Ensure water circulates
- Will be painful so need analgesia
- Dress with sterile non adherent dressings
- Elevate and splint limb
- Ensure tetanus up to date
- Consider infusion of tpA
- Consider hyperbaric oxygen
- Surgery delayed as long as possible waiting for tissue to demarcate. Early surgery has been shown to have increased rates of amputation
- Only acute indication for surgery is compartment syndrome
Chemical Injury
- Cause damage to living tissue through number of mechanisms
- Heat liberation from exothermic reactions
- Liquefactive necrosis by alkali
- Dilapidation by petrochemicals
- Vesicle formation by gasses
- Severity related to type, concentration, amount, and duration of contact
- Initial treatment is copious and prolonged irrigation with water
Electrical Injury
- Direct tissue injury
- Conversion to thermal energy at site of entry and along planes of conduction
- As a consequence of current density
- Deeper tissues cool more slowly than superficial tissues
- Get deeper injury
- Entry wound usually heavily charred
- At low voltages this will prevent further current flow
- Major injuries generally occur in limb soft tissue (muscle)
- Leads to myoglobinuria and renal failure
- Hyperkalaemia and acute renal failure can also occur
- Can get Compartment Syndrome
- Can also get
- Cardiac arrest
- Central and peripheral nervous injury
- Visceral injury
- Spinal compression fractures
Ionizing Radiation Injury
- Uncommon source of acute injury
- Radiation disperses energy as it travels through tissue
- Energy ionises molecules and starts chain of events that leads to damage to
- DNA
- RNA
- Cellular fibres
- Cellular membranes
- Get cell death, chromosomal rearrangements, point mutations
- Individual cells more susceptible if the divide more frequently
- Radiation endarteritis causes progressive devascularisation and fibrosis
- Affects wound healing and wound breakdown
- Late manifestations may include
- Radiation induced malignancies
- Radiation osteonecrosis
- Underlying organ damage
- Very high dose radiation exposure
- Widespread proliferative cell death
- Host defence breakdown (gut, immune system) leading to death
Normal Wound Healing

Phases
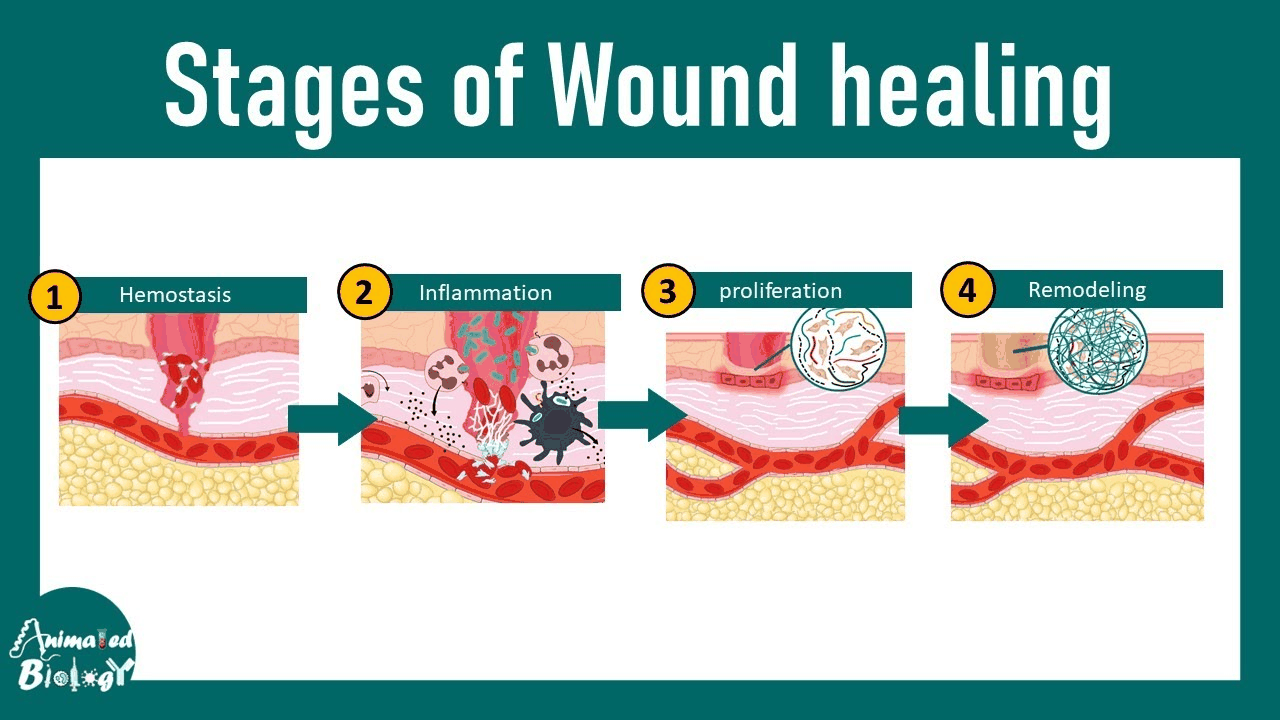
1. Haemostatsis
- Injury leads to platelet adhesion and activation with clot formation
- Stop bleeding
2. Inflammatory
- Clot stops bleeding
- But also provides matrix rich in growth factors and chemokines
- Acts as a scaffold for migrating leukocytes and stromal cells
- Also get inflammatory vascular changes followed by inflammatory cell recruitment
- Within 24hrs neutrophils appear at the margins
- Begin process of wound sterilization and debris degradation
- Granulation tissue
- Within 1-2 days (peak 5-7 days)
- Fibroblasts and endothelium form this
- Highly vascularised loose connective tissue and hallmark of early tissue repair
- Vessels leaky, therefore tissue oedema occurs
- At this stage, wound strength will primarily rely on sutures
3. Proliferative
- Migration and expansion of:
- Parenchymal cells (re-epithelialisation)
- Endothelial cells (Angiogenesis)
- Connective tissue cells (provisional matrix)
- Within 2-4 days, neutrophils largely replaced by macrophages
- Become main cellular elements in clearing debris and directing subsequent angiogenesis and ECM deposition
- Eventually granulation tissue scaffolding is converted to scar composed of fibroblasts and collagen
- Fibroblast migration and proliferation driven by macrophages
- TGF-β most important fibrogenic agent
- Fibroblast migration and proliferation driven by macrophages
- After 2 weeks, scar formation (collagen deposition) is the most dominant feature
- Get regression of the vasculature
- Granulation tissue all converted to avascular scar, without inflammation, covered by intact epithelium
- Get rapid increase in wound strength to 30-50%
4. Remodeling Phase
- Constant absorption and replacement of collagen along the lines of stress
- Wound contraction accomplished by myofibroblasts
- Have synthetic function of fibroblasts
- Also contractile capability of smooth muscle cells
- Cause decreased surface area of the wound
- Remodelling/change in ECM deposition
Strength of Wound Over Time
- Initially dependent on suturing
- At 1 week (when sutures removed)
- Typically has 10% strength of normal
- Tensile strength eventually plateaus at 70-80% of normal at 3 months
- Associated with increased collagen synthesis exceeding collagen degradation
- Followed by cross-linking and increased fibre size
Factors that Affect Wound Healing
-
Local Factors
- Ischaemia
- Tension
- Dead Space
- Foreign Bodies and contamination
- Wound infection
- Haematoma
- Local Trauma
- Chronic tissue factors – Lymphoedema, past scarring
- Sutures – too tight, silk (inflammation)
- Irradiation
-
Systemic Factors
- Age
- Medical comorbidities - Obesity, CRF, hepatic failure, diabetes
- Anaemia or blood loss
- Shock, hypovolaemia, hypoxia
- Malnutrition
- Septicaemia
- Advanced malignancy
- Immunosuppression and steroid use
- Chemotherapy
- Smoking
-
Abnormalities of Wound Healing
- Deficient Scar
- Inadequate granulation tissue or collage deposition
- Leads to wound dehiscence or ulceration
- Keloid and hypertrophic scar
- Atrophic Scar
- Surgery, trauma, acne vulgaris & varicella
- Responds well to laser
- Contracture Scar
- Result of contractile wound healing process in a scar that has already been re-epithelialize and adequately healed
- Normal, but exaggerated, part of the healing process
- Typically appear as a fixed, rigid scar
- Contributes to both cosmetic and functional problems
- Limits joint mobility
- Deficient Scar