- Definition
- HIT associated with thrombosis (paradoxical)
- Mainly associated with unfractionated heparin but can occur with LMWH
- Onset rare after 14 days
- Type 1 (MILD)
- Clinically insignificant, mild, transient drop in platelet count
- Incidence: 10-20%
- Aetiology
- Non-immune, Heparin induced platelet response to aggregating stimuli
- Clinical
- Insignificant - not related with thrombosis
- Rapid onset, 1-5/7 after commencement of Rx
- Platelet counts fall to 100-150 (NB: Platelet count could drop by 50% but still be in normal range)
- Management
- Continue Heparin and monitor
- May find a relative heparin resistance (i.e. higher doses to achieve therapeutic APTT)
- Return to normal within 1-5 /7 in spite of continued heparinisation
- Type II
- Associated with limb & life threatening complications
- HITTS (HIT + thrombosis syndrome)
- Incidence 0-30%
- 10% of Type II will develop thromboembolic complications (1% overall)
- Aetiology
- Immune related
- Caused by autoantibodies to platelet factor 4 (РF4)
- Antibody activates platelets and can cause catastrophic arterial and venous thrоmbοѕis
- Activated platelets release microparticles which accelerates Thrombin generation ⇒ Thrombosis (venous & arterial)
- Antiphospholipid syndrome potentially higher risk
- Immune related
- Clinical
- 6/7 after commencement of Rx, unless previous exposure
- Features
- Pain
- Skin necrosis
- Lower limb thrombosis
- MI
- Renal artery/vein thrombosis
- Thrombosis often localised to area with pre-existing arterial disease
- Diagnosis
- Acute drop in platelets
- Platelets < 50 x 109/L (if < 10 think of another process such as DIC)
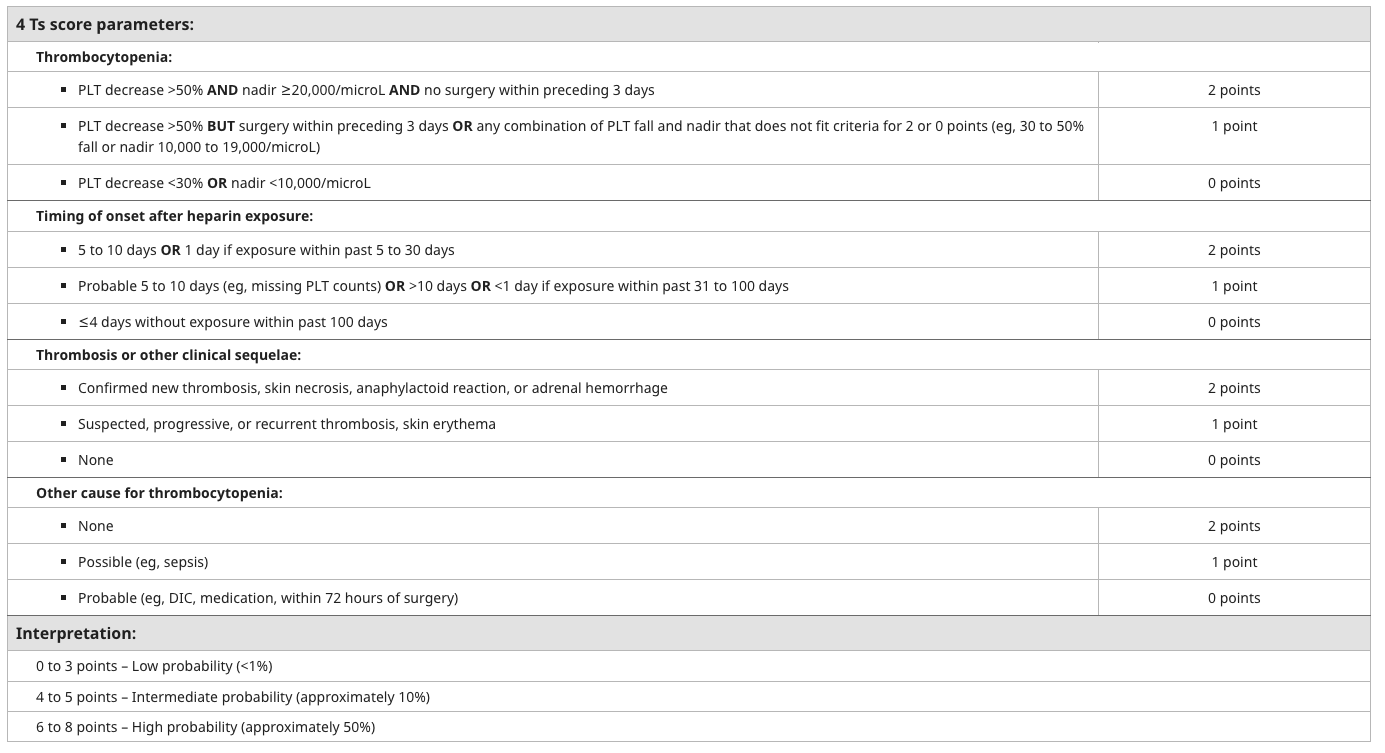
- 4 Ts score for estimating the pretest probability
- Can confirmed by immunoassay assays
- Count usually recovers in 5/7 after cessation of Rx
- Platelet count related to chance of thromboembolic complications
- Acute drop in platelets
- Prognosis
- HIT complicated by thromboembolism; Morbidity 22-80%; Mortality 12-30%
- Platelets usually recover within 2 weeks of heparin stopping
- Antibodies usually disappear within 3 months but recommended against further heparin
- Management
- Immediate
- Stop Heparin/LMWH - substitute with Thrombin Inhibitor (lepirudin – derivative of hirudin the anticoagulant in the saliva of leeches) or factor 10a inhibitor (danaparoid)
- If on, Stop Warfarin and reverse with vitamin K
- Full-dose therapeutic anticoagulation with a non-hepаriո anticoagulant rather than discontinuing heparin alone or discontinuing hеpariո and providing a prophylactic dose of a non-hepаrin anticoagulant
- Investigate other causes of decreased platelets
- Surgical thrombectomy
- Immunoglobulin aspirin, plasmapheresis
- Immediate
4 Ts score for estimating the pretest probability of heparin-induced thrombocytopenia (HIT)