- Incidence 1/200,000 live births.
- Association w other hepatobiliary disease such as hepatic fibrosis & aberrant pancreatico-biliary duct junction
- Presentation usually childhood w jaundice, fever or abdo mass. 25% diagnosed in 1st yr.
Pathogensis
- Possibly caused by anomalous biliary and pancreatic junction, causing pancreas juice to flow backward into bile duct causing cysts to form.
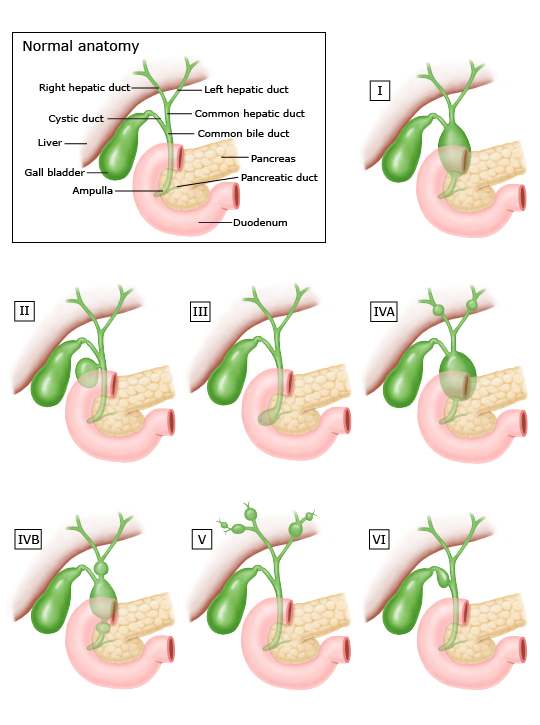
Modified Todani classification
- Type I: Fusiform dilation of the common bile duct
- Type II: Bile duct diverticulum
- Type III: Saccular dilation of the common bile duct in the ampulla, also termed choledochocele
- Type IV: Multiple cystic bile duct dilations
- Type IVA: Intra- and extrahepatic cysts
- Type IVB: Extrahepatic cysts only - Type V: Fusiform or saccular cystic dilation of the intrahepatic bile ducts, whether or not associated with hepatic fibrosis (Caroli disease)
- Type VI: Isolated cystic dilations of the cyst duct
Investigations
- MRCP best test
- ERCP
- EUS
Management:
- Initial mx – sepsis with abx, imaging, ERCP +/- stent
- Surgical resection to
- Prevent recurrent episodes of sepsis and pain,
- Prevent risk of pancreatitis (passage of debris and calculi)
- Prevent cholangiocarcinoma (Risk of malignancy ~12% or higher)
- Type I and IVb
- Complete cyst excision with preservation of pancreatic duct, w hepaticojejunostomy for reconstruction.
- Some recommend liver resection for type IVa with intrahepatic extension for complete removal of cyst, although advantage is debatable.
- Type II
- Simple excision
- Type III
- Can be treated endoscopically if close to the sphincter with a sphincterotomy
- Otherwise require Pancreatoduodenectomy
- Type IVa and V
- Caroli disease,
- Resect if disease localised to one part of liver.
- For others, endoscopic or radiological techniques may be needed to improve biliary drainage.
- Some may need transplant if liver failure.
- Intraoperative ultrasound useful to find biliary confluence, intrahepatic extension of cyst and relationship to right hepatic artery above & pancreatic duct below.
- Small aberrant ducts may enter cyst, easier to identify once cyst is opened along anterior length.
- Segmental ducts incorporated into hepatico-jejunal Roux-en-Y anastomosis.
Surveillance:
- Postop: annual USS and Ca 19-9 to detect stenosis, stones or malignancy
- If not resected, annual MRI + MCRP