- Often had cholecystectomy, middle aged, female
Recurrent abdominal pain after cholecystectomy
- Three types:
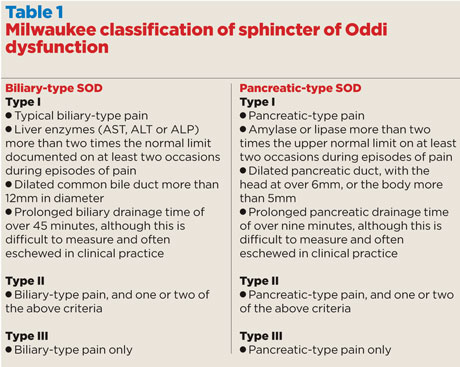
- Type 1 – abdominal pain, obstructive LFTs, biliary dilatation and delayed emptying of contrast at ERCP
- Type 2 – pain with only one or two of above
- Type 3 – recurrent biliary pain
- Diagnosis usually by exclusion. Morphine-neostigmine and secretin provocation MRCP may be of diagnostic value.
- Biliary manometry should be reserved for patients whose diagnosis is unclear (type 2)
- Medical therapy with calcium channel blockers, nitrates and botox is available, long term results unknown.
- Avoidance of opioid may prevent onset of pain. Development of pain following codeine is diagnostic.
- ERCP potential treatment. 5-16% post ERCP pancreatitis. Good responses in 69%.
- Surgical sphincterotomy, only if ERCP unsuccessful.