- Overview
- Type of implant reconstruction reconstruction
- Direct to implant
- Delayed (two stage) - tissue expander first then exchange for an implant at a second operation
- Indications
- Patient want a reconstruction
- Non-smoker
- Normal BMI <30 or <35
- Non-diabetic/well controlled
- Does not require radiation
- Typically early breast cancer (so does not need radiation)
- Can have neoadjuvent treatment first
- Risk
- Delaying further treatment - if needs adjuvant chemo and has a complication
- Nipple necrosis
- Is it arterial vs venous
- Warm blanket, warm room, bare hugger
- GTN patch
- Heparin injections into flap
- Preparation
- Same as mastectomy
- Prepare bilaterally as when you do the reconstruction you need to compare to other side
- Sterility is very paramount given implant
- Incision
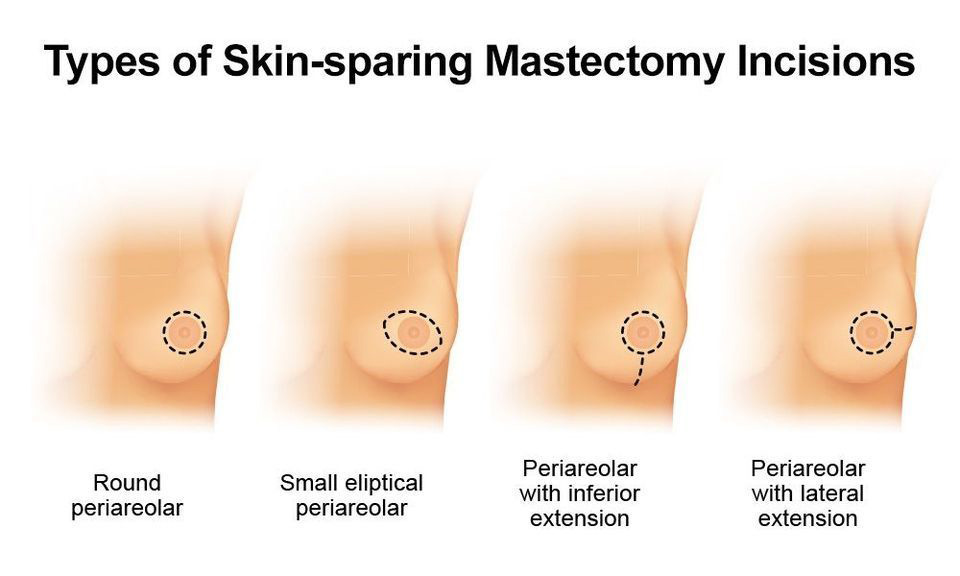
- Different incisions
- Skin sparing
- Elliptical excision of NAD gives you access to everywhere
- Usually second picture as circular incision not normally fonr
- Nipple sparing
- Wise pattern (third picture) or lateral extension incision (fourth picture )
- Both you can only cut around 50% of NAC otherwise necrosis
- Infra-mammary line incision is also an option
- Dissection
- Raise mastectomy flaps sharp or diathermy
- Pit falls
- Lateral superior/axilla tail is the most difficult to get to hence why the lateral incision variant is often done
- Wise patten incision allows you to do a symmetrising wise pattern breast reduction on the other side with the same scar