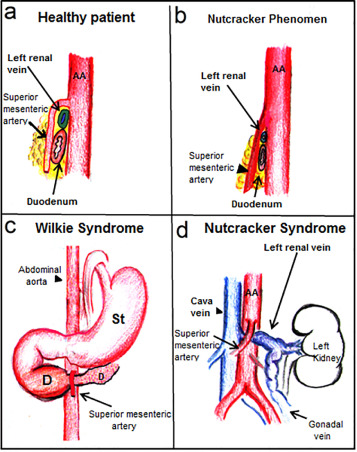
Definition
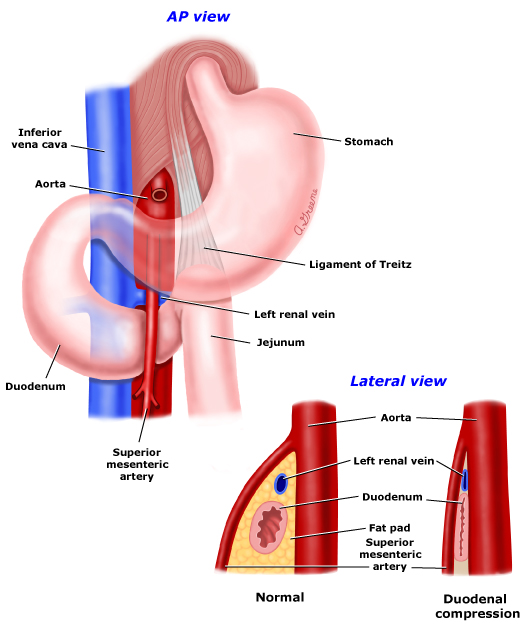
- Extrinsic compression of D3 between SMA and aorta
- Can result in duodenal obstruction
Incidence
- Rare
- F>M
- Young adults
Aetiology
- Congenital (things that close the angle
- High insertion of duodenum at ligament of Trietz
- Low SMA origin
- Adhesions
- Rapid weight loss
- Trauma
- Spinal disease, deformity or direct trauma
Pathophysiology
- Normal SMA-aorta angle is approximately 45 degrees
- D3 cross from right to left between SMA and aorta
- Just caudal of SMA origin
- Left renal vein also within this angle!
- Anything that causes angulation to drop below 25 degrees causes D3 extrinsic compression
- Most common cause is rapid weight loss and reduction in size of mesenteric fat pad between SMA and aorta causes narrowing of the angle
Clinical
- Acute/chronic partial obstruction
- Post prandial pain
- Bilious vomiting
- Weight loss
- Relief of sx with left lateral decubitus positioning?
Investigations
- CTA with sagittal views
- Criteria for SMA
- Aortomesenteric angle <22 degrees
- Aortomesenteric distance <10mm
- OGD to R/O other causes of obstruction
- Barium swallow - dilated D1 and D2, delayed gastric emptying, antiperistaltic waves
Management
- Acute
- NGT, resuscitation, IVF, electrolyte replacement
- Non surgical
- NJT/TPN
- Attempt to increase the size of the aortomesenteric fat pad to increase the angle and relieve obstruction
- 4-6 weeks at least
- Surgical
- Indications
- Failure of non-operative management
- Options
- Strong’s procedure
- DJF flexure mobilisation
- Division of ligament of Trietz
- Position duodenum to RIGHT of SMA
- 25% recurrence rate
- Does not involve division or bypass of duo
- Gastrojejunostomy
- Can get blind loop syndrome or peptic ulceration
- Duodenojejunostomy +/- division of D4/proximal jejunum
- Can get blind loop syndrome if D4 divided
- Strong’s procedure
- Indications

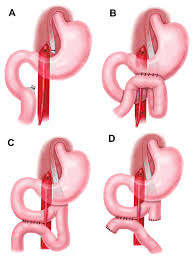 Surgical operations for SMA syndrome. A. Strong’s procedure. B. Gastrojejunostomy. C. Duodenojejunostomy is accomplished without division. This is the preferred surgery; or with D. Not recommended as the best option since there is division of the 4th portion of the duodenum