Section: Surgical Oncology Curriculum: Curriculum, page 64
Also see: Breast screening
Principles of Screening for malignancy
- Screening of a population is used to detect disease in individuals without signs & symptoms of that disease.
- The aim is early detection thus enabling early intervention & management in the hope to reduce mortality & morbidity,
Issues
- Overdiagnosis – PSA – more men die with prostate cancer than of it
- False positive
- Misdiagnosis
- False sense of security – false negative
- Cost & use of medical resources
- Adverse effects from screening – stress & anxiety, discomfort, radiation exposure, chemical exposure
- Adverse effects from further Ix in false positive (ie: biopsy)
Biases
- Lead-time bias
- Two people, one screened, one not, the non-screened one picked up on symptoms 6 months later. Both die same day, it could look like screened patient had survival advantage as had longer survival from diagnosis
- Length bias – screening more likely to pick up slower growing tumours
- Selection bias – there will be differences in those that choose to take up screening
Types
- Universal screening – screening of all individuals in a certain category
- Case finding – screening a smaller group based on the presence of risk factors (family member been diagnosed with a hereditary disease)
WHO principles of population screening
- Important health problem
- Recognisable latent or early symptomatic stage
- The natural history is understood
- Accepted treatment
- Suitable test or examination that has a high level of accuracy
- Test should be acceptable to the population
- Agreed policy on whom to treat as patients
- Facilities for diagnosis and treatment should be available
- Cost of screening should be economically balanced in relation to possible expenditure on medical care as a whole
- Screening should be a continuing process
NZ screening tests
- Foetal – eg PKU, hypothyroidism, CF, congenital adrenal hyperplasia (CAH)
- Breast cancer screening
- cervical cancer screening
- Mantoux for Tb
- FOB & Colonoscopy
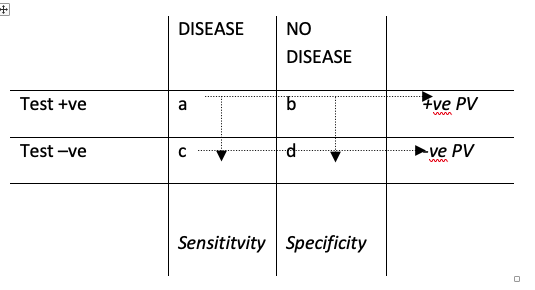
Sensitivity & Specificity
- sensitivity = proportion of people with the disease who test positive (a/a+c)
- specificity = proportion of people without the disease who test negative (d/d+b)
- +ve predictive value = chance that people have the disease if they test positive (a/a+b)
- increases when the prevalence in a population is high
- -ve predictive value = chance that people don’t have the disease if they test -ve (c/c+d)
- increases when the prevalence in a population is low