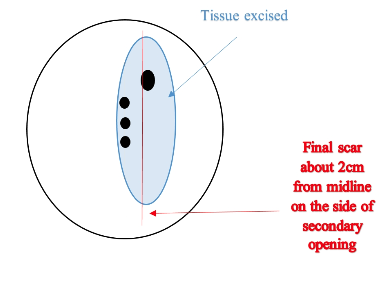
The principle of this operation is to excise the pits and lateral extension with an off midline incision which creates a more shallow natal cleft
- Mark buttock
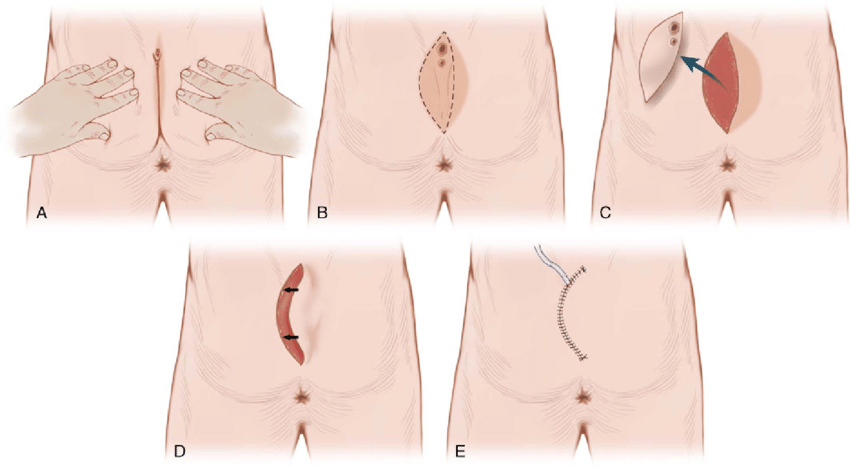
- While the patient is standing, the buttocks are compressed medially, and the line of contact between the two sides of the gluteal skin is marked. The depth of cleft is measured
- The skin is shaved and the buttocks are taped apart to facilitate access to the inferior margin of the gluteal cleft.
- Incision
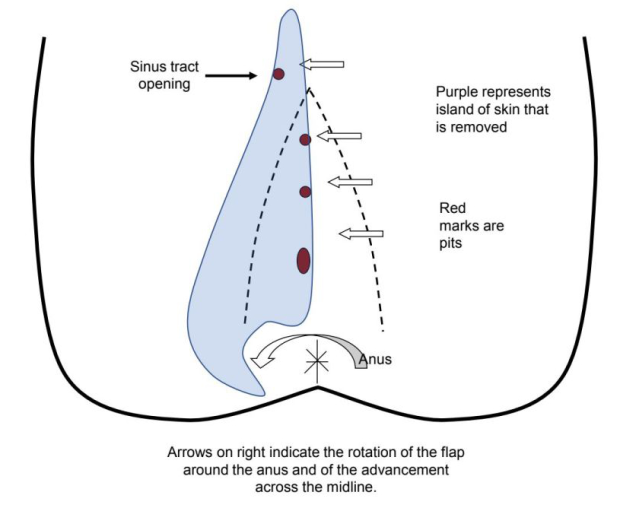
- An off-centre, elliptical incision mark is drawn vertically to make the cleft shallower and flatter.
- Long-acting local anaesthetic is injected into the operative field.
- The first incision incorporates all of the damaged skin to be removed.
- It is crucial to preserve as much skin around the anus as possible.
- Create flap
- An advancement skin flap, approximately 1 cm thickness, is elevated from the medial side of the incision.
- Once the flap has been raised, the tapes on the buttocks are removed, and the flap is checked for sufficient stretching.
- Excise disease
- Subsequently, the island of the skin on the opposite side, is removed and all sinus tracts, debris and hair are removed. It i
- Close
- Adipose tissue is sutured with interrupted 2–0 (Vicryl™) absorbable sutures.
- Before the incision is approximated, a 7 mm Jackson-pratt drain is placed at the surgical site.
- Subcutaneous tissue is sutured with 3–0 absorbable sutures (Vicryl™). The skin is closed with synthetic absorbable monofilament (4–0 Monocryl™) subcuticular suture.
 Source: codi16701-sup-0001-videos1
https://onlinelibrary.wiley.com/doi/10.1111/codi.16701