How I Do It- Side-to-Side Isoperistaltic Strictureplasty for Extensive Crohn’s Disease, page 1
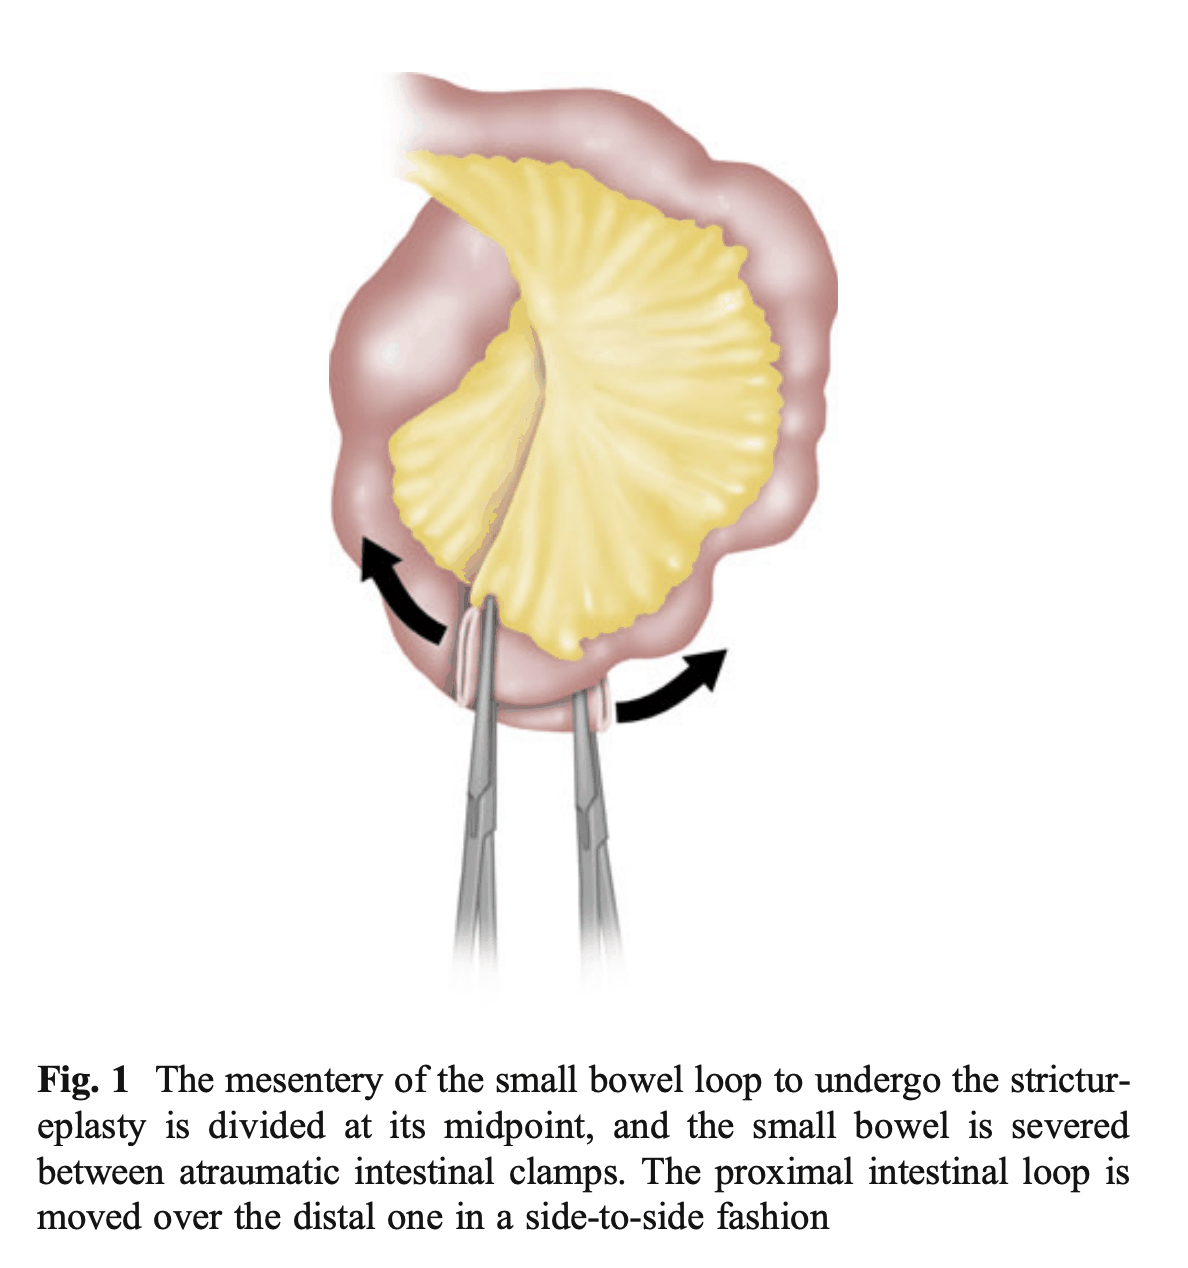
- Mesentery and small bowel is divided at the midpoint of the stricture (fig 1)
- The bowel is then overlapped. Care is taken to ensure that stenotic areas of one loop are opposed to the dilated areas of the other loop, in order to avoid creation of narrow points. (fig 1)
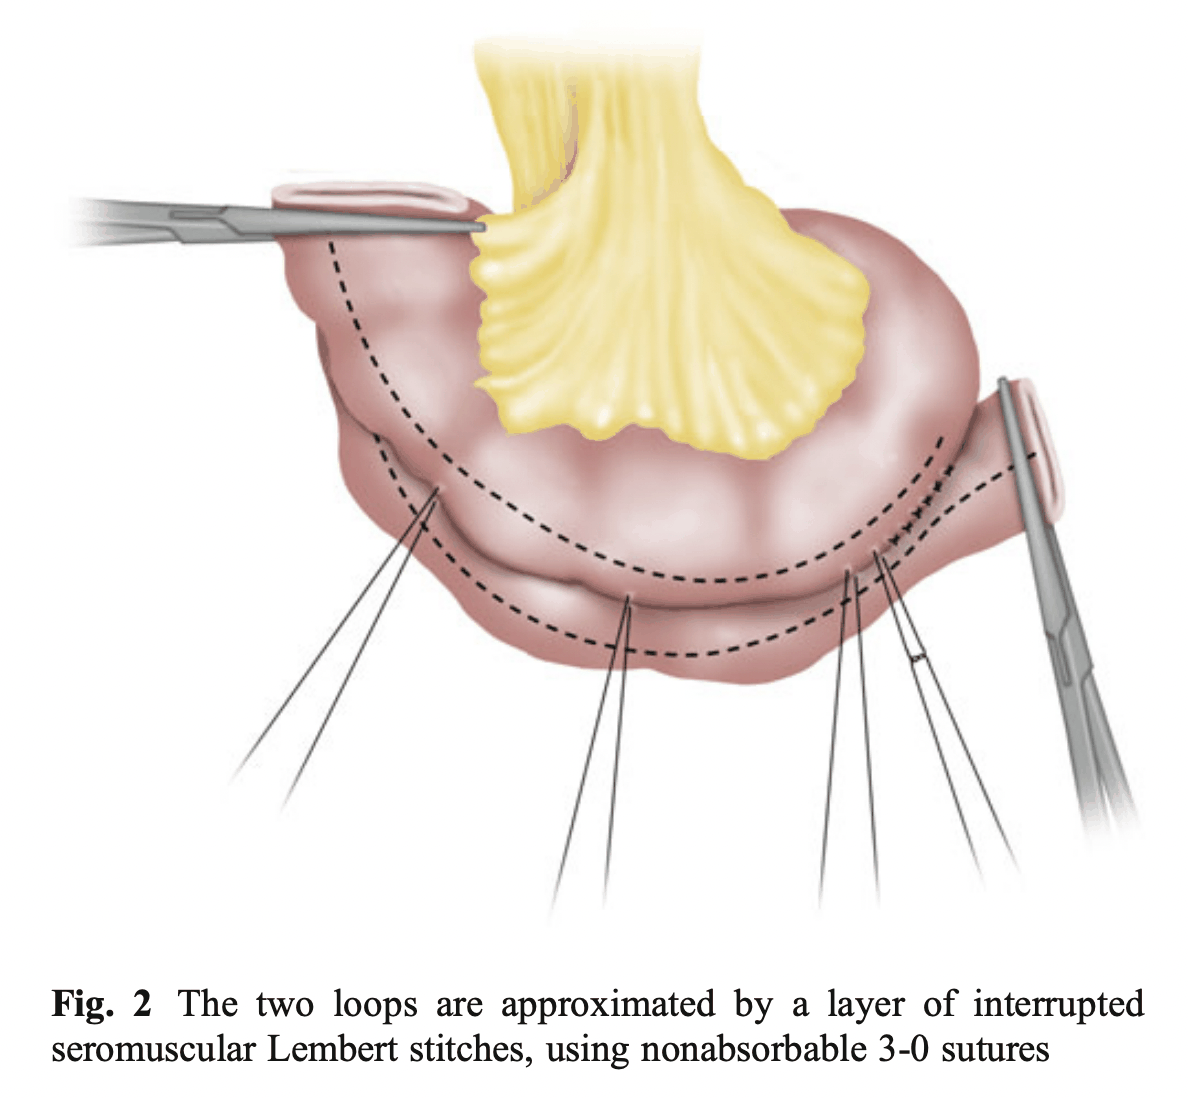
- The two loops are then approximated by a layer of interrupted seromuscular Lembert stitches, using nonabsorbable 3-0 sutures (fig 2)
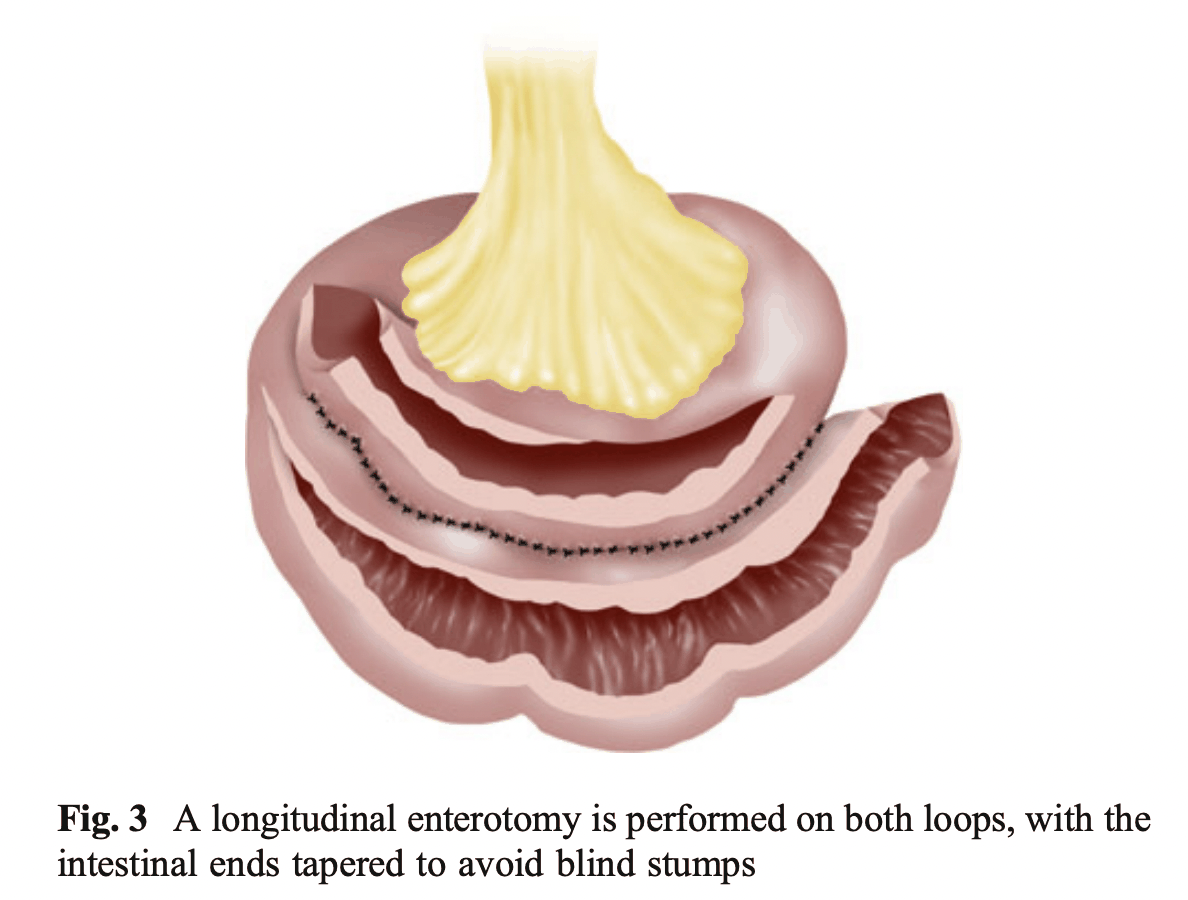
- A longitudinal enterotomy is performed on both loops, with the intestinal ends tapered to avoid blind stumps (Fig. 3).
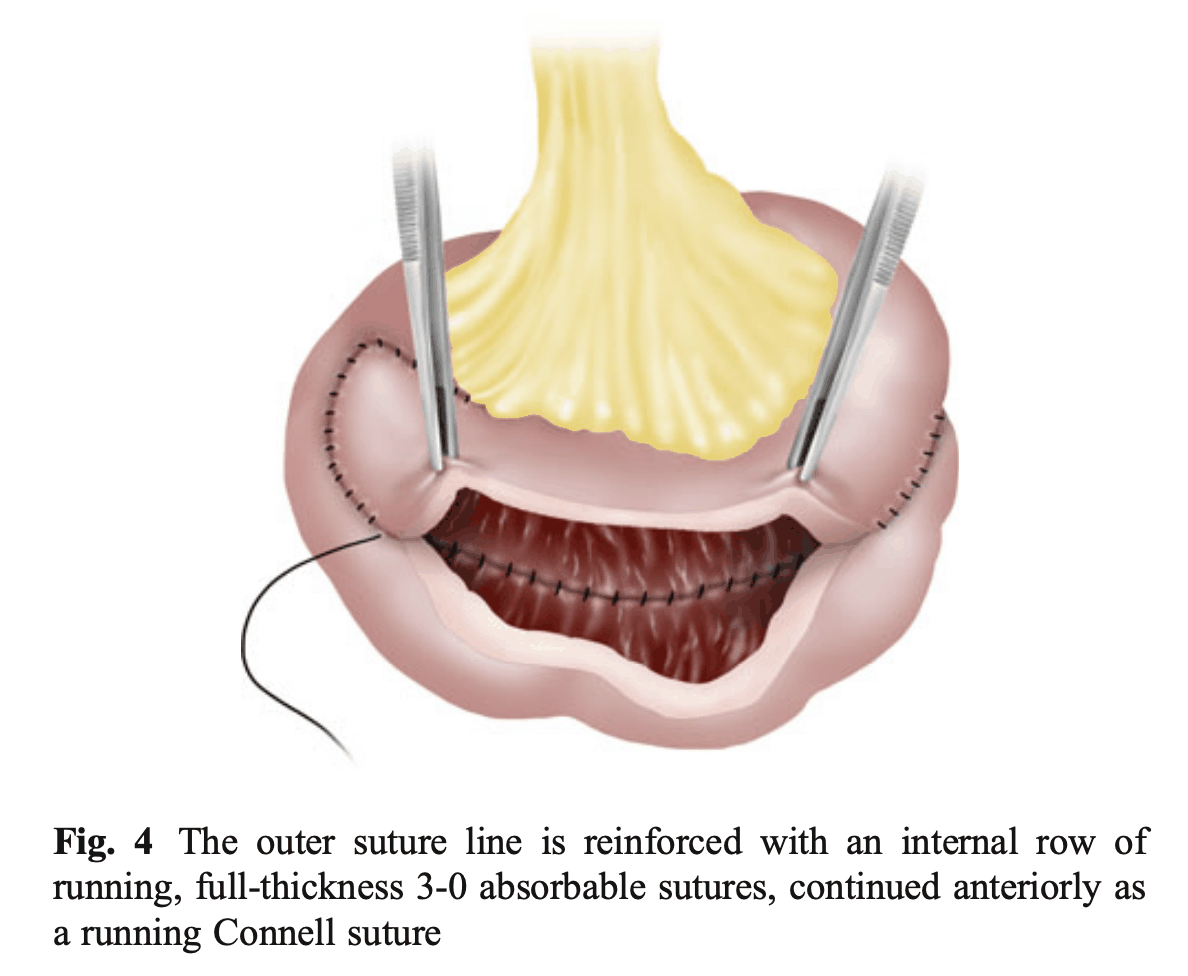
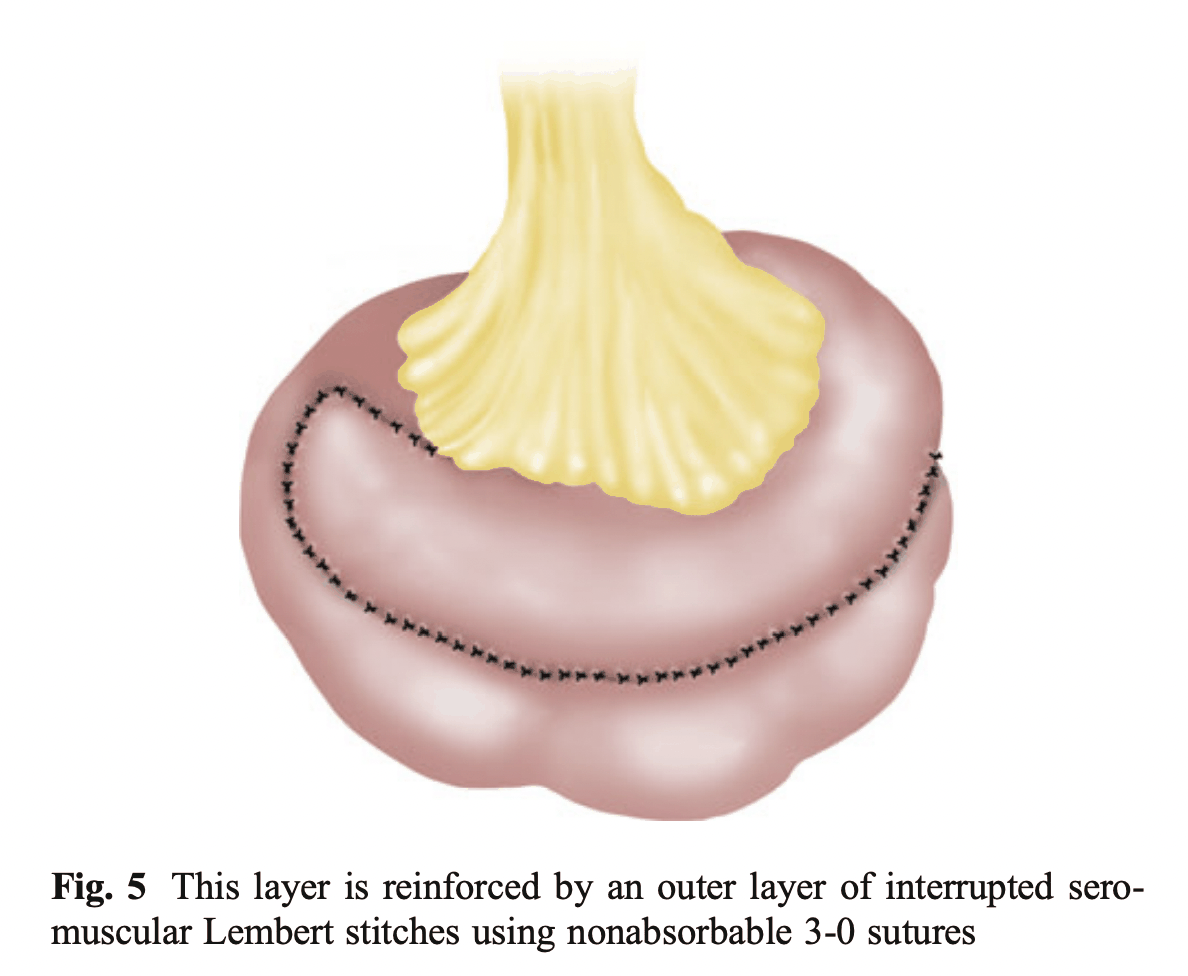
- The outer suture line is reinforced with an internal row of running, full-thickness 3-0 absorbable suturess, continued anteriorly as a running Connell suture (Fig. 4); this layer is reinforced by an outer layer of interrupted seromuscular Lembert stitches using nonabsorbable 3-0 sutures (Fig. 5).