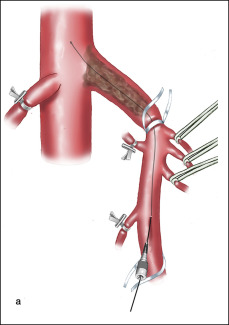
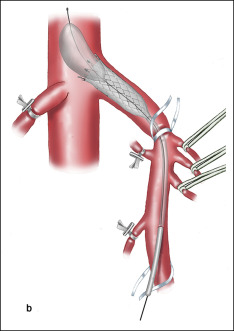
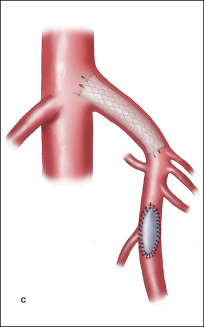
- Set up as for Embolectomy of the Superior Mesenteric Artery
- Retrograde stenting in patients with atheromatous lesions.
- Once exposure as above
- Collateral branches of the SMA are identified and looped with vascular tapes.
- The artery is punctured, and the introducer is inserted
- The introducer should be chosen according to the type and size of endovascular material envisioned and as long as possible
- A 0.035 hydrophilic guide is then replaced by a stiff guide to stabilize the subsequent maneuvers and is passed through the obstructing lesion after previous dilation by a small size balloon (3–4 mm).
- The size of the stent is chosen according to the diameter of the vessel.
- The flared end is inserted into the aorta, to ensure the best hemodynamics
- Arteriography is performed to control the efficacy of the stent placement
- After purging the stent, the introducer entry point is repaired, either by direct suture, or patch plasty