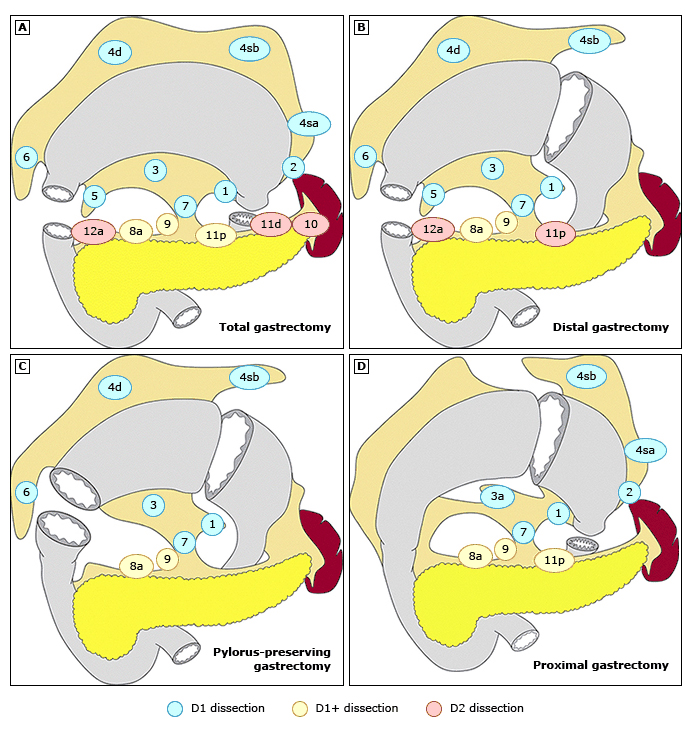
At NSH we perform a D1 plus = 1-7 + 8 and 9 as standard
- At least 16 LN are necessary to accurately stage a tumour
- T1a tumours 3% LN involvement
- T1b = 18% involvement
- T4a = 80% involvement
- Controversy re: limited vs extended LN dissection
- Removal of at least the Station 1-6 -level nodes (D1) improves 5-yr survival (20 → 34%)
- D3 = D2 + D3 – not recommended!
- Dutch Gastric Cancer Group Trial phase III:
- D1 vs D2 5yr survival rates similar (~ 45%)
- D2 Disadvantages
- More post-op complications (45 vs 30%)
- More post-op deaths (10% vs 5%)
- Longer hospital stays
- D2 Advantages
- Survival difference in patients with N2 / stage II & IIIA disease (D2 better)
- Risk of recurrence greater in D1 than D2 group (40 vs 30%)
- Unfortunately, ‘N2’ disease cannot be reliably identified pre-op
- Greatest contributing factor to post-op M&M in D2 group was addition of pancreaticosplenectomy
- “D2 resection without pancreaticosplenectomy may be better than a standard D1”
- Other Western studies
- Survival benefit for D2 without pancreaticosplenectomy
- Italian Gastric Cancer study Group (IGCSG), Austrian study, Spain - Post-op mortality after D2 ≈ 3-5%
- ANZGOSA recommendation
- Splenectomy if greater curvature involved with tumour
- Distal pancreatectomy only if direct tumour involvement
D1 Resection
- Early gastric cancer (T1) should be treated with D1 gastrectomy
- D1 dissection entails gastrectomy and the resection of both the greater and lesser omenta
- Stations 1 to 6 (+ now includes 7, left gastric)
- Includes the lymph nodes along
- Right (1) and Left (2) cardiac
- Lesser (3) and Greater (4) Curvature
- Suprapyloric (5) along the Right Gastric Artery
- Infrapyloric area (6)
D1 Plus Resection
- D1 plus
- Levels 7, 8a, 9
- Standard of care for Stages II & IIIa because
- Safe (provided pancreaticosplenectomy not done)
- Gives prognostic information
- Japanese survival stats – D2 mortality <1%
D2 Resection
- D2 dissection is a D1 plus all the nodes along the left gastric artery, common hepatic artery, celiac artery, splenic hilum, and splenic artery
- Station 7
- Left Gastric Artery (N1) – should be removed in all gastrectomy (including distal)
- Station 8
- Common Hepatic Artery (N2)
- Station 9
- Coeliac Trunk (N2)
- Station 10
- Splenic Hilum (N2)
- Not necessary to resect for all cancers, as often diff to resect without splenectomy
- Recommended for proximal gastric cancers on greater curvature
- Station 11
- Splenic Artery
- Station 12
- Hepatoduodenal nodes
- Hepatoduodenal nodes