-
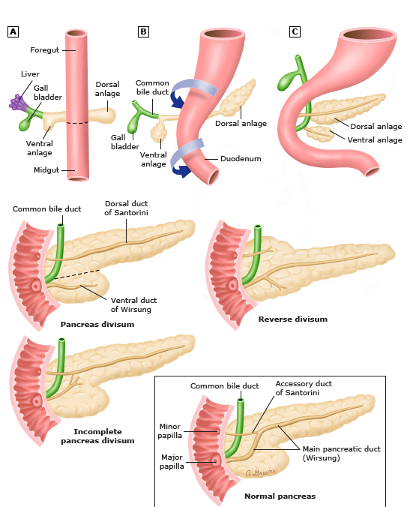
Persistence of the dorsal accessory pancreatic duct (of Santorini) with no connection with the main ventral duct (of Wirsung)
-
Failure of fusion of ventral & dorsal ducts in the embryonic pancreas
-
Means main pancreas drains through minor papilla
-
Commonest congenital pancreatic abnormality: 6-10%
-
Found in ≈ 25% of pts with otherwise unexplained pancreatitis
-
Implicated as a cause of acute pancreatitis
-
? Small / stenotic minor papilla → Intermittent obstruction by proteinaceous plugs
-
Investigations - MRCP / ERCP
-
Management: Recurrent acute pancreatitis may benefit from
-
ERCP & sphincterotomy of minor papilla
-
± Pancreatic stone extraction / lithotripsy
-
Fewer than 5 percent of patients with pancreas divisum are symptomatic.
-
Most symptomatic patients have infrequent bouts of pancreatobiliary-type pain or develop mild acute pancreatitis.
-
Subset of symptomatic patients with pancreas divisum have recurrent pancreatobiliary-type pain, severe acute pancreatitis, chronic pancreatitis associated with clinically significant disability due to chronic abdominal pain or pancreatic insufficiency, or pancreatitis-associated complications (eg, pseudocyst)
-
Pathologic narrowing of the minor papillary orifice. This results in excessively high intrapancreatic dorsal ductal pressure during active secretion, which may result in inadequate drainage, ductal distension, pain, and in some cases, pancreatitis.
-
Imaging modality of choice is Secretin-enhanced MRCP
Treatment
- Asymptomatic - ignore
- Symptomatic - sphincterotomy (surgical or endoscopic)