-
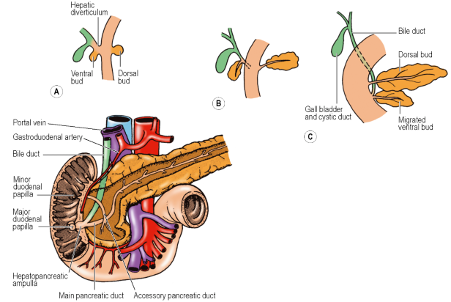
Pancreatic buds (week 4)
- Develops as 2 separate buds – each an outgrowth of the Endoderm at the junction of the Foregut and Midgut
- Occurs between 4th and 8th weeks of development
- Ventral bud:
- Grows in the Ventral Mesogastrium in common with the outgrowth of the Bile Duct
- Rotates 270 degrees
- Dorsal bud:
- Grows independently from a separate duct into the Dorsal Mesogastrium
- Rotates 90 degrees
-
Rotation and fusion (week 6)
- The duodenum undergoes rotation during development, causing the ventral pancreatic bud to rotate and move dorsally.
- Fusion of the dorsal and ventral pancreatic buds occurs, forming the mature pancreas.
- Tail, Body, Neck and part of the Head develop from the Dorsal bud
- Rest of the Head and Uncinate Process develop from the Ventral bud
-
Duct systems of the two buds anastomose
- Duodenal end of the Dorsal Duct becomes the Accessory Pancreatic Duct
- Duodenal end of the Ventral Duct joins the remainder of the Dorsal Duct to form the Main Pancreatic Duct
-
Pancreatic acini – develop by growth of cells from terminal parts of the branching ducts
-
Islet cells – identical origin but become separated from their parent ducts and undergo a complete change of secretory function
Abnormalities of Pancreatic Development
Annular Pancreas
- Partial or complete circumferential encasement of 2nd part of the duodenum by a band of pancreatic tissue
- Prevalence: 3 per 20,000
- Aetiology: Migration anomaly – failure of the ventral bud to rotate
- Clinical: Most remain asymptomatic during lifetime
- Other possible symptoms:
- Duodenal constriction – non-bilious vomiting, bloating, feeding intolerance
- Pancreatitis
Pancreatic divisum
- Persistence of the dorsal accessory pancreatic duct (of Santorini) with no connection with the main ventral duct (of Wirsung)
- Failure of fusion of ventral & dorsal ducts in the embryonic pancreas
- Means main pancreas drains through minor papilla
- Commonest congenital pancreatic abnormality: 6-10%
- Found in ≈ 25% of pts with otherwise unexplained pancreatitis
- Implicated as a cause of acute pancreatitis
- ? Small / stenotic minor papilla → Intermittent obstruction by proteinaceous plugs
- Investigations - MRCP / ERCP
- Management: Recurrent acute pancreatitis may benefit from
- ERCP & sphincterotomy of minor papilla
- ± Pancreatic stone extraction / lithotripsy