Key principles
- Longer femoral stump results in better control of prosthesis
- Perform a myodesis if possible anchoring muscles to femur
- If unlikely to walk make stump short
- Ensure good skin and muscle coverage
Specific preoperative preparation
- Mark out incision with equal anterior and posterior flaps
- 12cm from knee joint for flap apex
- 2 finger breaths from patella for distal extent of anterior flap
- “Fish-mouth” incision
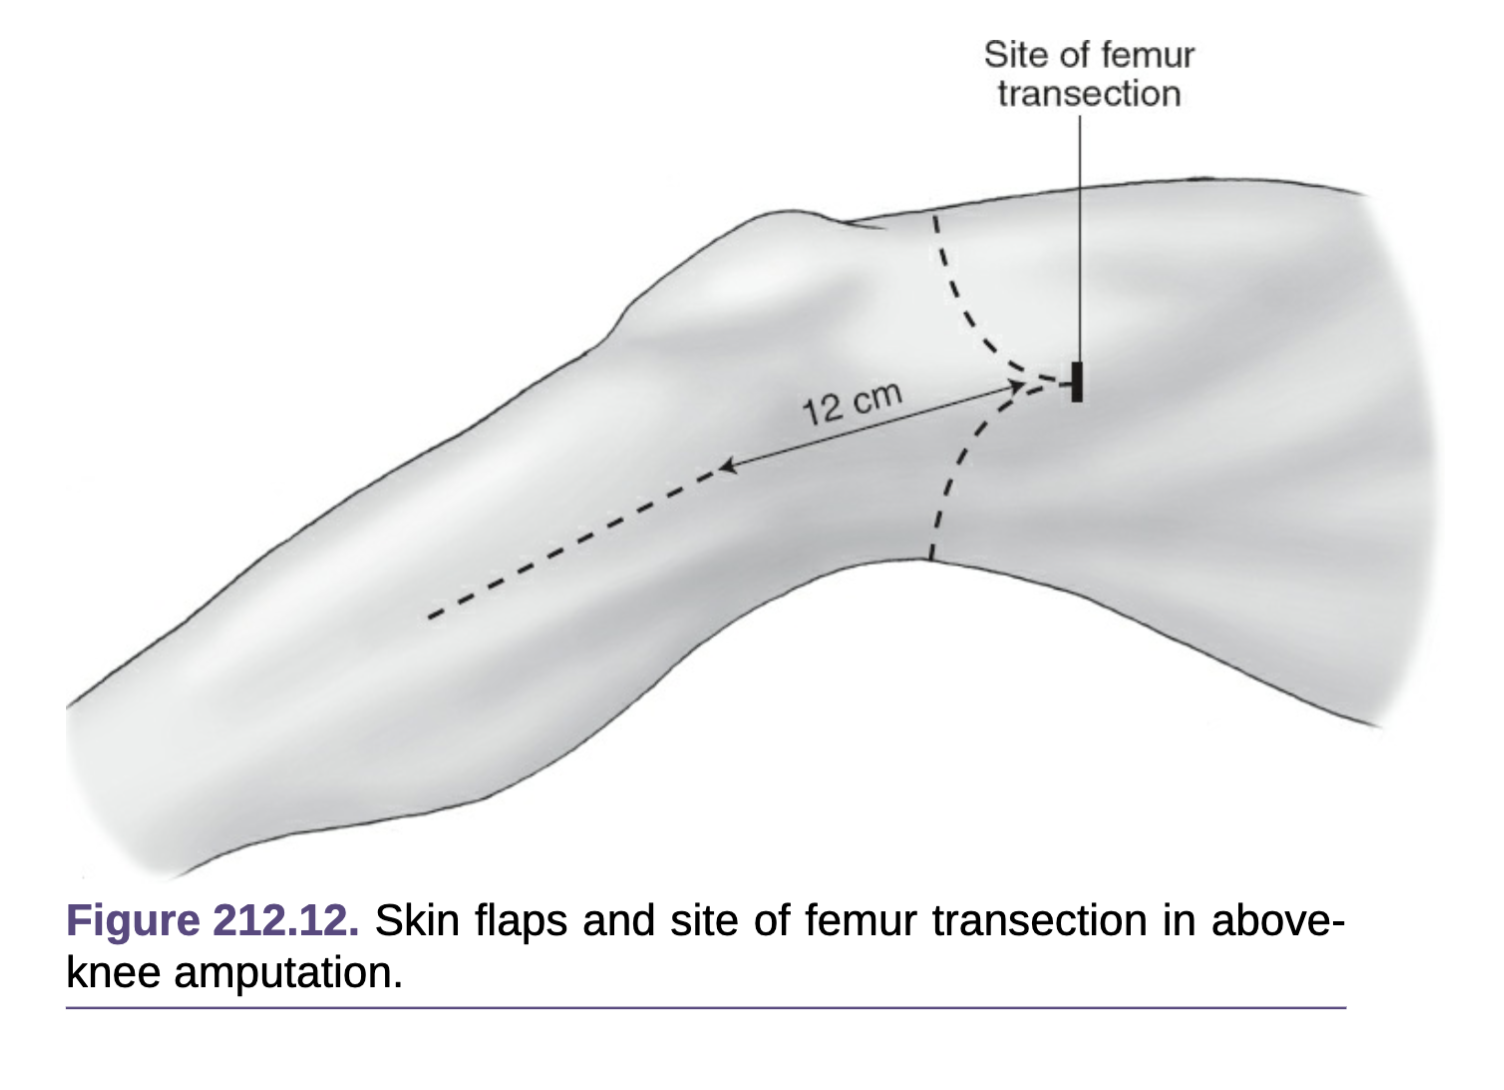
Operation Details
- Can be performed under regional or general anaesthesia.
- Supine with sandbag beneath buttocks
- Prep and free drape leg. Foot in bag
- Divide skin and subcutaneous tissue taking care to identify and ligate GSV with 2/0 vicryl ties
- Divide anterior muscle down to bone at level of femoral transection
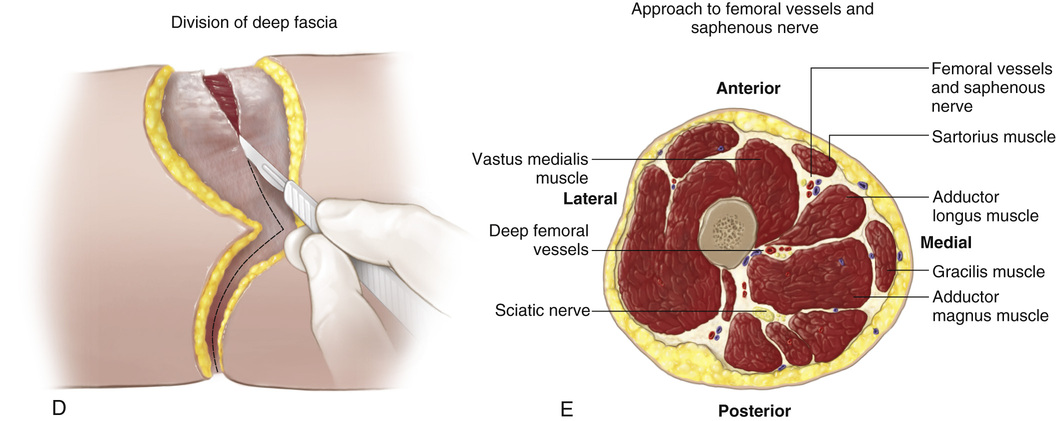
- Identify femoral vessels beneath Sartorius and doubly ligate with 1 vicryl ties
- Divide periosteum and cut through bone with Gigli saw
- Retract distal femoral fragment to allow identification of profunda vessels and sciatic nerve.
- Divide and doubly ligate profundal vessels. Ligate sciatic nerve under tension and divide it cleanly - can place a pain catheter into it directly for post op pain relief
- Divide posterior muscles and remove limb
- Haemostasis
- Round off bone ends with rasp and apply bone wax
- If performing myodesis drill a small hole in posterior cortex femoral stump and suture
- quadriceps with 2/0 vicryl
- Close fascia 0 vicryl
- Place suction drain exiting laterally
- Close skin with 3/0 Nylon and apply steristrips
- Bandage with crepe
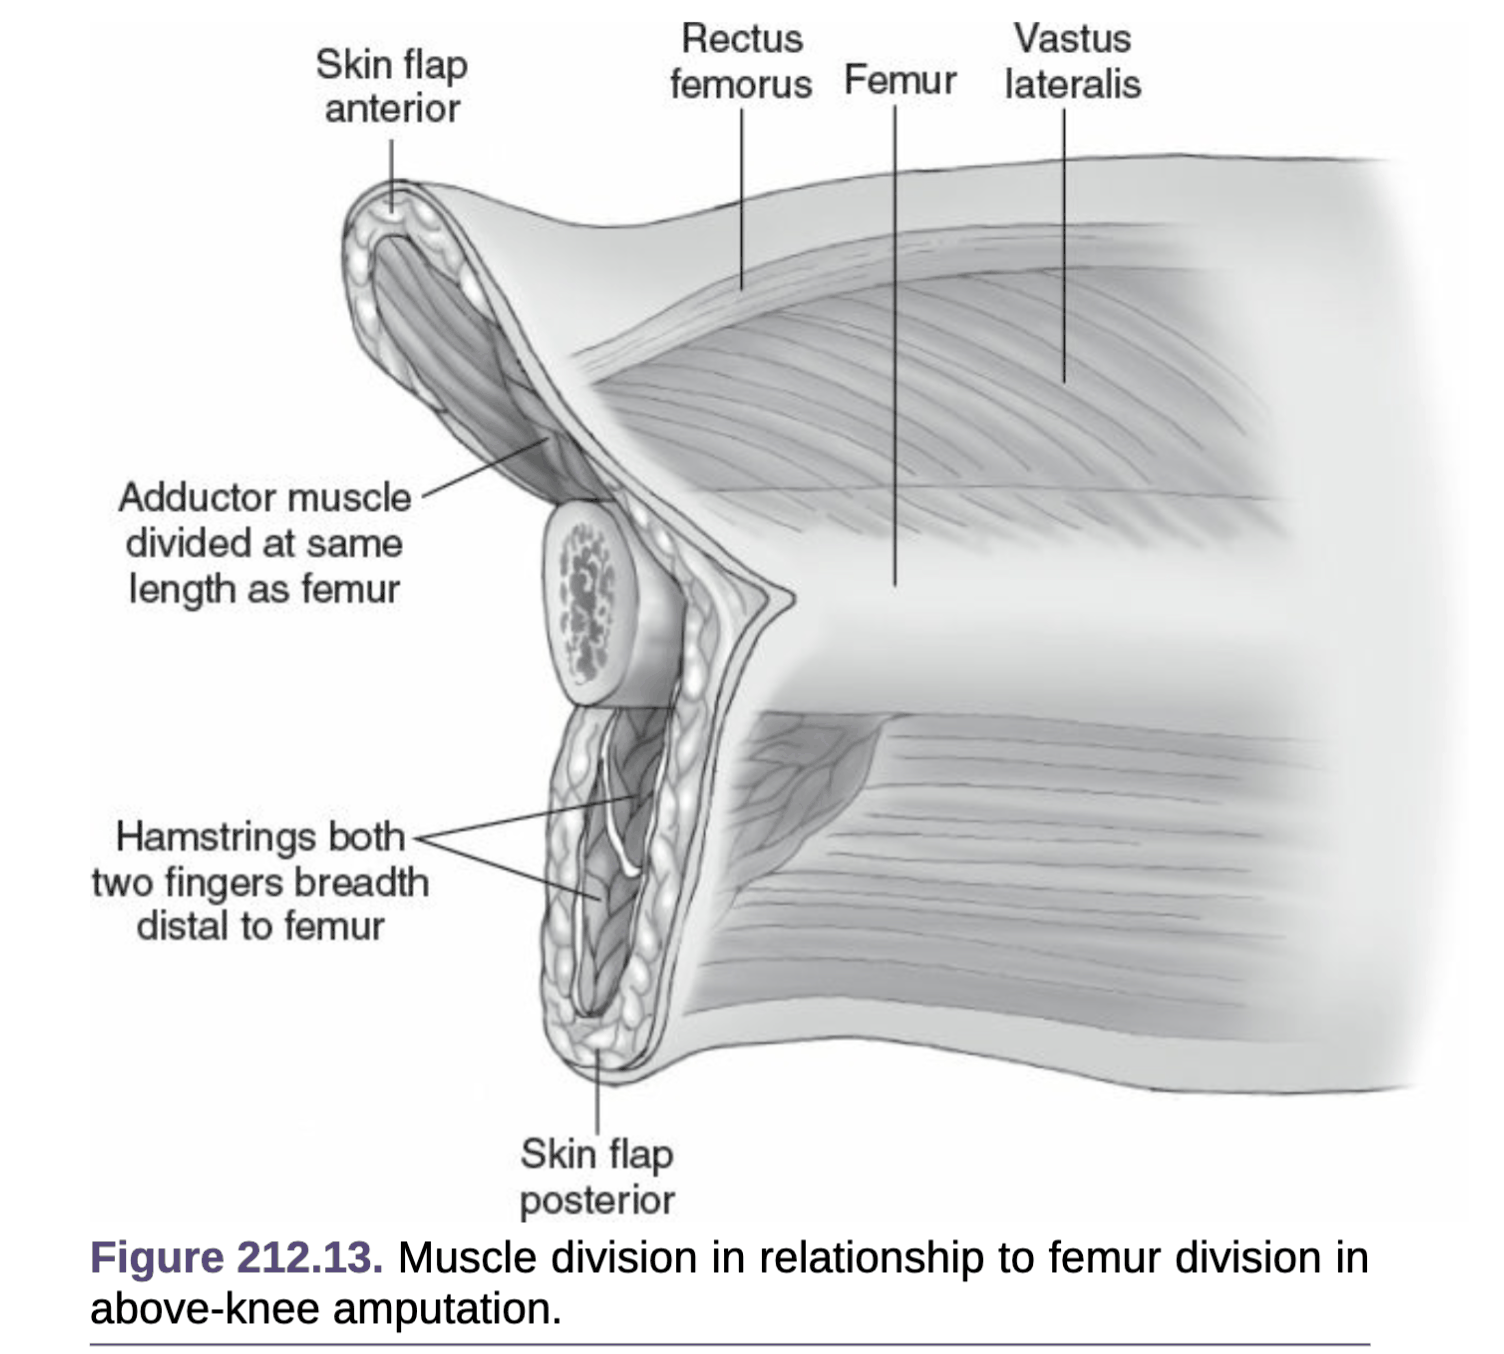
Relative anatomy
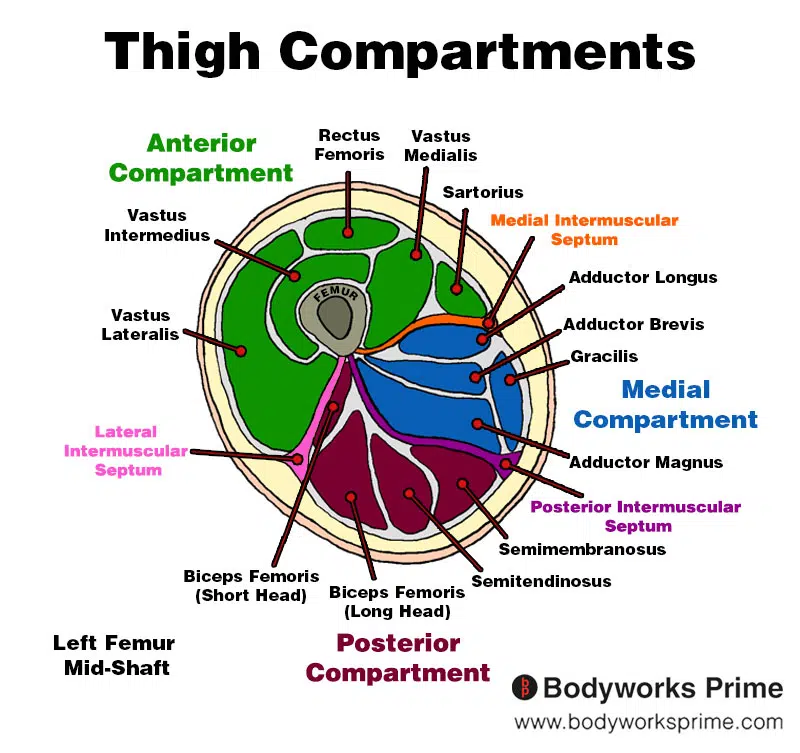
- Thigh divided into 3 compartments
- Quadriceps and Sartorius in anterior compartment with SFA and saphenous nerve
- Adductors and pectineus in medial compartment
- Hamstrings, profunda femoris and sciatic nerve in posterior compartment
Post-operative complications
- Early
- Bleeding
- Infection
- Stump breakdown / Flap necrosis
- Late
- Phantom pain
- Neuromas
- Erosion
Specific post-operative care
- Remove drain 48 hours
- Regular physiotherapy
- Remove sutures 14 days
- Apply firm stump bandage at 2 weeks, temporary pylon at 3-4th weeks and definitive limb at 6-12 weeks