Section: UGI Sub-section: Bariatrics Curriculum: Curriculum, page 83
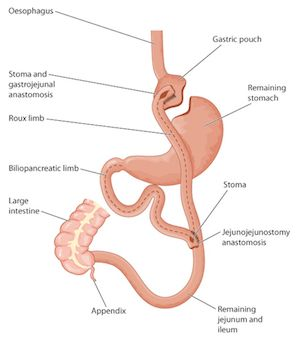
- Roux-en-Y gastrojejunostomy anastomoses the remnant stomach to an isoperistaltic roux limb of jejunum
- The proximal jejunum (BP limb) is anastomosed to the distal Roux limb in an end-to-side fashion.
- Does not preserve duodenal or jejunal continuity
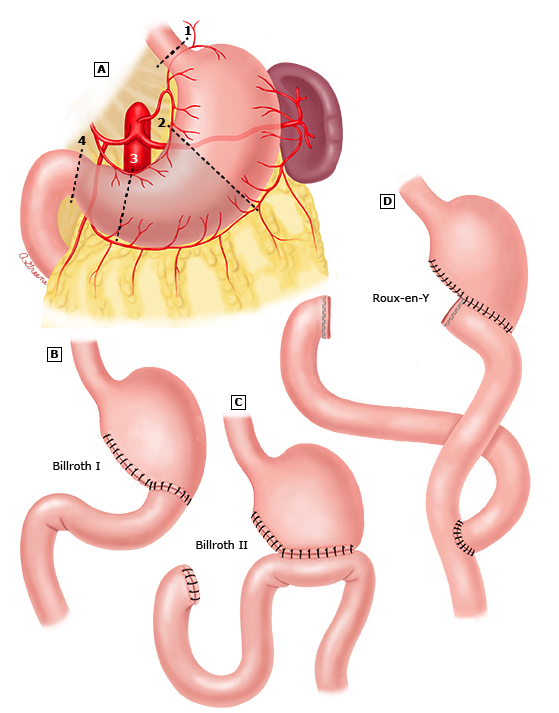
Roux–en–Y Gastric bypass
Principles
- Both malabsorptive & restrictive procedure
- Prophylactic Cholecystectomy recommended if gallstones
- ERCP post-op is impossible in these patients; gallstone risk is high
- Roux-limb should be at least 75cm-150cm in length (length debated)
- BP limb should be at least 50cm from DJ flexure (between 50-100cm)
- After Gastric Bypass
- All patients started on
- Multivitamins
- B12 / Folate / Iron regularly tested and supplemented as required
- All patients started on
Mechanism of Weight Loss
- Primarily restrictive due to small pouch
- Malabsorptive component adds to weight loss
- Gastrojejunostomy anatomy
- Leads to dumping physiology
- Has negative conditioning response against high-sugar diet
- Roux-limb (Alimentary) length
- Optimal length disputed
- Balance between weight reduction and malabsorption
- Increased length = Malabsorption due to decreasing length of common channel
- Should not be > 150cm
- Ghrelin
- Normal pulsatile release inhibited in RYGB due to the foregut bypass configuration
- Also seen in Sleeve Gastrectomy
- May contribute to appetite suppression
- NB: Over time Ghrelin levels may increase back to normal
- Normal pulsatile release inhibited in RYGB due to the foregut bypass configuration
- Other Hormones
- GLP-1 and CCK may also promote anorectic state
Procedure
- Trochar placement
- Creation of small lesser curve gastric pouch
- Blunt dissection 4-6cm from GOJ to enter lesser sac
- 45mm stapler fired obliquely
- Blunt dissect the retrogastric attachments aiming to the angle of His
- Pass Bugie
- 2-3x 60cm stapler firing towards Angle of His to complete 20cc pouch
- Measure BP limb
- Lift transverse colon up to identify DJ flexure
- Measure 50cm
- Fire 60cm stapler
- Take a small amount of mesentery in-between
- Mark BP limb - stitch or clip or burn
- Measure Roux limb
- Measure 90-150cm
- Create jejunpjejunostomy
- Create a stapled or hand sewn JJ
- Place anti-obstruction stitch
- Close mesenteric defect by continuing running this stitch down
- Create gastrojejunostomy
- Pass the Roux limb retro- or anti-colic
- Create the GJ - stapled or hand-sewen
- Trim Candy Cane limb if required
- Close mesenteric defects

Pros and Cons
- Pros
- Effective for weight loss and comorbidities
- 50-60% EWL at 3 yrs
- T2DM in remission in 70%
- HTN resolved in 70%
- OSA resolved in 80%
- Improves GORD in 90% of cases (only bariatric surgery proven to do so)
- Improves gut hormone profile to reduce appetite
- PYY + GLP-1 induced satiety
- Less risk of malabsorption that BPD/DS
- But more than Gastric Sleeve or Band
- Partially reversible
- Cons:
- Steep learning curve
- Difficult to perform ERCP post-op
- Generally only recommended in high-volume centres
- Reasonable cost
- Longer operative time and longer inpatient admission
- Moderate complication rate
- 10% Morbidity rate
- 0.3 - 1% Mortality
Complications
- Early
- Leak 3% (usually at gastrojejunostomy or above)
- Staple line bleed 3%
- Stricture
- Roux-en-O configuration (requires re-do surgery)
- Late
- Internal Hernia 2% (usually months/years later)
- Stricture of Gastrojejunostomy up to 10%
- Gastric remnant distension
- Gastrogastric fistula
- Marginal ulcer 2-10%
- Dumping Syndrome
- Gallstones
- Candy-cane Roux
Laparoscopic vs Open RYGB
- Laparoscopic patients
- Less likely to have re-operations
- Less likely to have post-op complications, incl. leak
- Have shorter length of stay
- Lap Bypass vs Lap Band for obesity
- Small increase in early complications in bypass group
- More (delayed) complications in lap band group
- Less weight loss with lap band
- 50% vs 70% of EWL at 2-10yrs
- Modern Sleeve vs Modern RYGB
- Essentially equal in outcomes for co-morbidities except for REFLUX
- Sleeve also has poor outcomes for dyslipidaemia
Fobi Pouch Principles
- < 30mL vertical pouch (usually 5-10mL)
- Vertical orientation – less liable to distension
- Divided stomach
- Reinforced staple line by patching Roux limb along staple line
- 1-2cm outlet/anastomosis
- 6.5cm Silastic ring
- Prevents outlet widening with time
- Ring requires removal in 2%